
Dexcom: How Wearables Digitized Diabetes
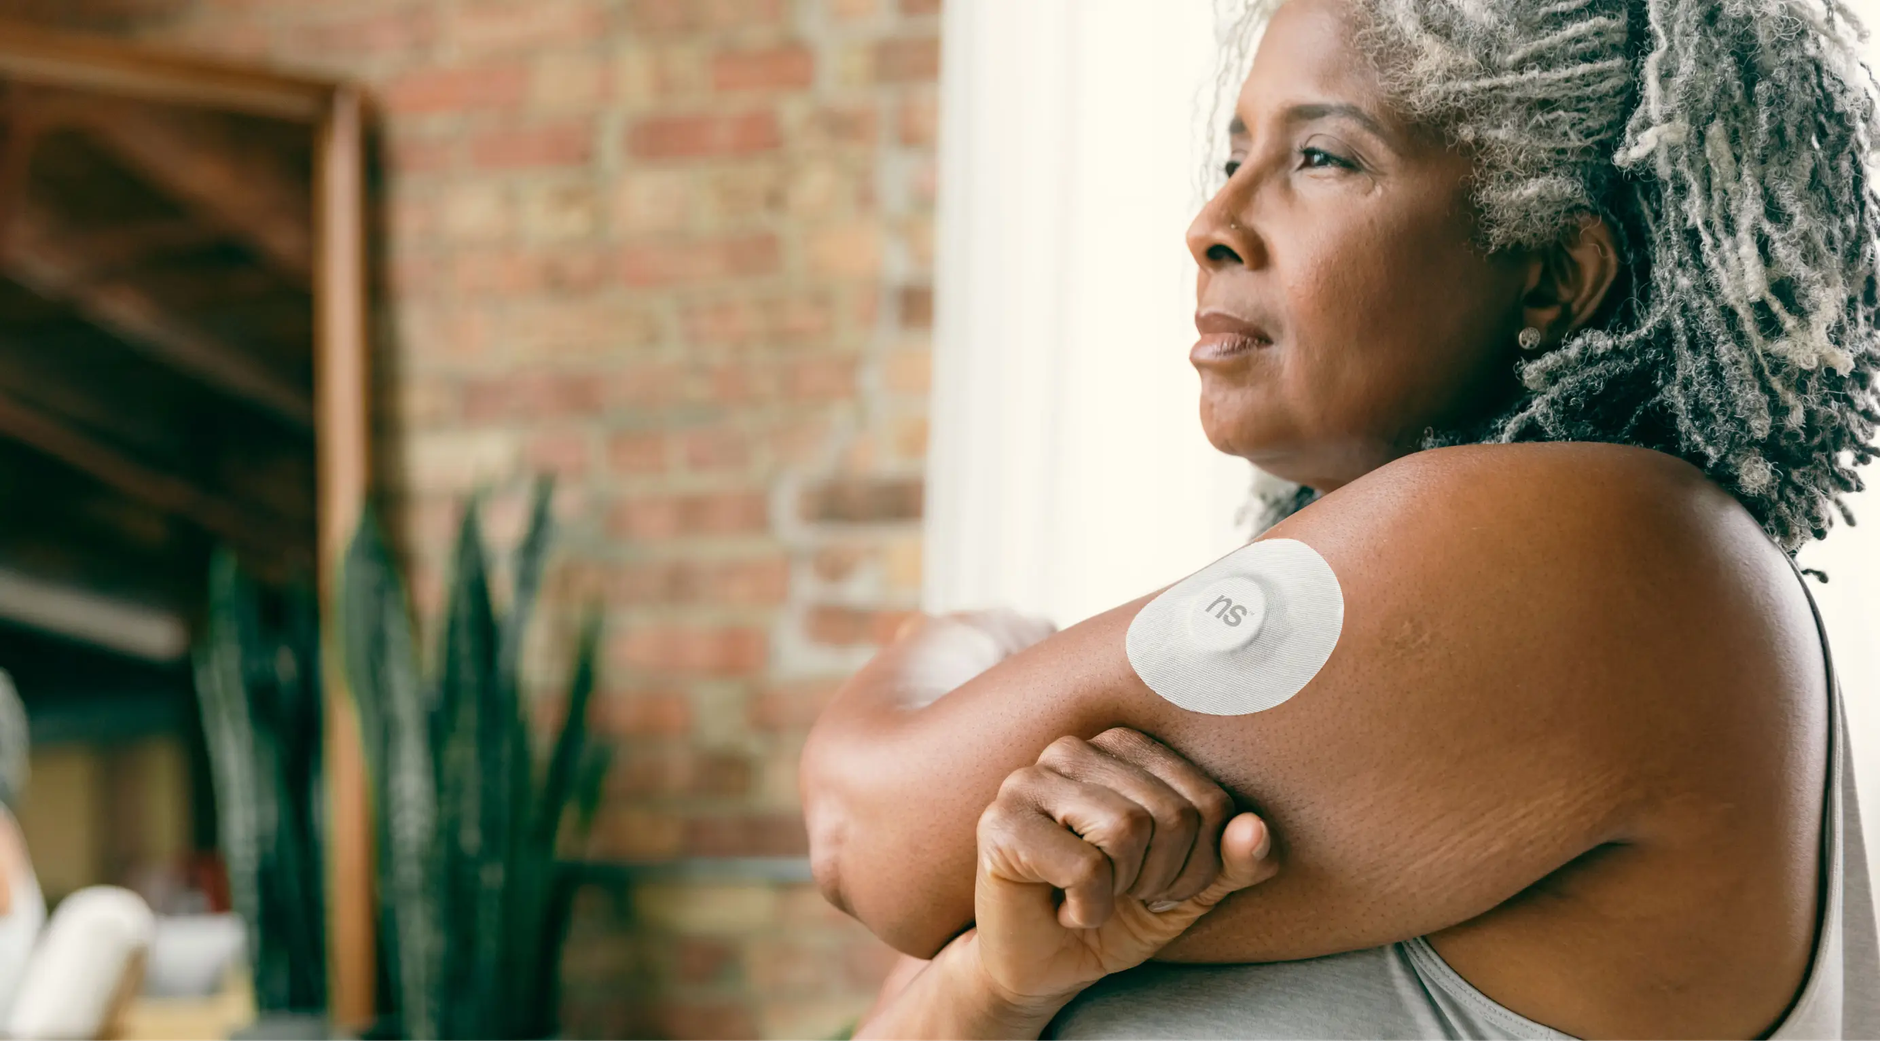
The patient becomes the factory. Every ten days, a 5-millimeter filament threads itself into the abdomen’s interstitial fluid, sampling glucose levels every five minutes through a bioelectrical process that converts chemical concentration into digital signal. The sensor, smaller now than two stacked quarters, adheres to the skin with industrial-grade adhesive meant to survive showers, workouts, and sleep. After 240 hours, it dies, and the patient peels it off, disposing of several dollars’ worth of platinum-group metals, microelectronics, and sterile packaging. Then they insert another.
This is the economic engine of Dexcom: a consumables business masquerading as a medical device company, generating roughly $5 in revenue against $1.50 in manufacturing cost per wear cycle, yielding gross margins near 70%. The math works because the customer never stops consuming. Type 1 diabetics require intensive insulin management until they die; Type 2 patients on intensive regimens face decades of monitoring. Insurance companies, commercial plans paying approximately $2,000 annually, Medicare closer to $2,500, foot the bill not because they are generous, but because they have calculated the alternative. Uncontrolled diabetes generates hospitalizations costing $17,000 to $30,000 per patient annually. Dexcom’s real-time alerts, predictive trend arrows, and 1.5% A1C reduction represent cheap insurance against catastrophe. The business model externalizes the manufacturing burden onto the patient’s body while internalizing the recurring revenue.
But this elegant mechanism contains a structural trap. Dexcom currently captures roughly 40% of Type 1 diabetics and 25% of the intensive Type 2 population in its addressable markets. These are high-acuity, high-compliance patients where the clinical case writes itself. The theoretical total addressable market, $120 billion if you include all pre-diabetics, gestational diabetes, and non-intensive Type 2 patients, dangles before management like a mirage. To reach it, Dexcom must convince insurers to reimburse $2,000 annual monitoring costs for populations where the risk of immediate diabetic crisis is lower, where the 1.5% A1C improvement may not translate to measurable cost savings, and where patient compliance is less certain. The company has responded with direct-to-consumer Super Bowl advertisements featuring Nick Jonas, attempting to create patient pull that forces physician and payer hand. Yet this expansion risks destroying the very margin structure that funds the ecosystem integration necessary to defend against competition. Dexcom is attempting to bridge two incompatible businesses: the high-margin medical device serving the desperately ill, and the mass-market consumer health product serving the worried well.
The Manufacturing Barrier and the Duopoly’s Quiet Stability
Only three companies manufacture continuous glucose monitors at scale. Medtronic, the pioneer with FDA approval dating to 1999, still requires manual fingerstick calibration and lacks real-time transmitter integration, leaving it functionally obsolete for new prescriptions. Abbott owns the value segment with Libre, a cheaper, flash-based system lacking real-time alerts and insulin pump connectivity. Dexcom occupies the premium tier, commanding higher reimbursement through superior accuracy and ecosystem integration. This is not a competitive market; it is a duopoly sustained by manufacturing complexity that resembles semiconductor fabrication more than pharmaceutical production.
The sensor filament must be sterilized, enzymatically active, and electrochemically stable while remaining flexible enough to avoid tissue irritation. The transmitter must process nanoampere-level signals through proprietary algorithms that filter out motion artifacts, temperature fluctuations, and electromagnetic interference. Scaling this production requires clean rooms, regulatory validation for each manufacturing line change, and clinical trial data proving that lot-to-lot variation does not compromise the 8-10% Mean Absolute Relative Difference (MARD) accuracy standard. The “graveyard of CGMs” Novartis abandoned, GlucoWatch failed, and numerous startups suffocated under these requirements. Capital alone cannot solve this; Dexcom’s manufacturing moat represents a decade of accumulated process knowledge that would take years to replicate even with unlimited funding.
This barrier creates the first strategic tension: the duopoly is stable precisely because manufacturing invasive sensors is difficult, yet Dexcom’s entire value proposition depends on invasive technology remaining the clinical gold standard. The moment infrared spectroscopy, transdermal glucose extraction, or smart contact lenses achieve sub-15% MARD accuracy without breaking skin, Dexcom’s manufacturing complexity transforms from competitive advantage to operational anchor. Non-invasive monitoring would eliminate the consumables model entirely, o more ten-day replacement cycles, no more adhesive failures, no more filament insertions. Consumer electronics companies with distribution reaching billions rather than millions could enter overnight. Apple’s research into silicon photonics and Google’s work on glucose-sensing contact lenses represent existential threats not because they exist today, but because they map a future where Dexcom’s regulatory lead and manufacturing scale become irrelevant. The company is racing to entrench itself as a software platform before the hardware becomes commoditized by physics.
The Algorithm as Moat
Most analyses of Dexcom focus on the hardware: he shrinking size of the G7, the elimination of calibration fingersticks, the adhesive improvements. This misses the durable advantage. Dexcom’s true intellectual property lies in signal processing: the proprietary algorithms that convert low-amplitude electrochemical noise into accurate glucose readings with directional trend arrows.
Glucose oxidase enzymes embedded in the sensor filament generate electrical signals proportional to glucose concentration, but these signals drift with temperature, pH, and sensor degradation. Competitors require users to calibrate against fingerstick blood glucose readings to correct this drift. Dexcom’s calibration algorithm automates this correction through factory calibration and real-time signal processing that accounts for individual physiological variation. More importantly, the algorithm improves with data. Every sensor worn contributes to training datasets that refine the predictive models. This creates a data flywheel: more patients generate more data, improving accuracy, which attracts more patients.
Abbott’s Libre lacks the real-time transmitter necessary for predictive alerts and insulin pump integration. Medtronic’s Guardian requires calibration. Dexcom’s accuracy advantage, translating to the 1.5% A1C improvement that keeps patients out of hospitals, is not merely a feature gap but a widening trench. Competitors cannot license this capability; it requires simultaneous mastery of bioelectronics, statistical signal processing, and clinical validation through years of FDA-monitored trials. The moat is mathematical.
The Integration Trap
Dexcom’s strategic response to the hardware commoditization threat involves burrowing deeper into the diabetes management stack. The company has integrated with Tandem’s Control-IQ insulin pump to create closed-loop “artificial pancreas” systems where the CGM automatically adjusts basal insulin delivery. Integration with Omnipod’s tubeless pump follows. This creates formidable switching costs: a patient using a Dexcom-Tandem closed loop must switch both their sensor and their pump simultaneously, requiring new prescriptions, insurance re-authorization, and endocrinologist retraining.
Yet this integration introduces dependency. Dexcom becomes a component in someone else’s ecosystem. If Tandem were acquired by a major pharma company, or if Omnipod signed an exclusive deal with Abbott, Dexcom’s distribution would constrict overnight. Worse, if Apple or Google successfully launch non-invasive monitors, insulin pump manufacturers would likely prioritize integration with platforms offering superior patient data aggregation and consumer-grade user interfaces. Dexcom risks becoming the Intel of diabetes: premium component supplier in an industry moving toward integrated systems. The company’s recent partnerships with Livongo and Omada (remote diabetes management services) represent attempts to capture more of the patient journey, but these moves also fragment focus and require competencies in software and care coordination far removed from electrochemical sensor manufacturing.
The Reimbursement Gauntlet
Insurance companies, not patients, are Dexcom’s true customers. The patient pays little or nothing; one-third of Dexcom users have zero copay compared to 10% for Abbott Libre. This generosity extends only to insulin-intensive populations where the health economic case is bulletproof. For expansion into pre-diabetics and non-intensive Type 2 patients, markets four times larger than the current core, Dexcom must prove that $2,000 annual monitoring prevents downstream costs in populations where the baseline risk of hospitalization is already low.
This is where the DTC marketing strategy becomes economically perilous. The Nick Jonas Super Bowl advertisement and similar campaigns generate patient demand among populations where clinical utility is marginal. If a pre-diabetic patient demands a Dexcom, receives it through aggressive physician prescribing, but fails to modify behavior sufficiently to prevent progression to Type 2 diabetes, insurers absorb the cost without realizing the savings. Insurance companies respond to such misalignment by restricting coverage, demanding prior authorizations, or pressuring Dexcom to match Abbott’s lower pricing. The expansion into mass markets risks collapsing the 70% gross margin that funds the R&D necessary to maintain algorithmic superiority and ecosystem integration.
The health economic data remains ambiguous for lower-risk populations. While 1.5% A1C improvement is clinically significant for insulin-dependent patients, its translation to cost savings in pre-diabetics depends on behavioral modifications that CGMs alone cannot guarantee. Dexcom is betting that real-time biofeedback creates sufficient behavioral change to justify reimbursement, but insurance actuaries may conclude that cheaper, less frequent monitoring suffices for populations not facing immediate hypoglycemic risk. If reimbursement contracts for pre-diabetics, the $120 billion TAM contracts to the $20 billion current reality, and Dexcom becomes a mature medical device company growing at GDP rather than the 20% rates investors currently price.
The Hardware Finale and the Software Pivot
Kevin Sayer, Dexcom’s chief executive, has signaled that the G7 sensor, smaller, faster, factory-calibrated, represents the endpoint of major hardware innovation. Future value creation will shift toward software: algorithms, predictive analytics, and integration layers. This strategic pivot functions as an economic variable with profound implications for capital allocation and organizational capability.
Hardware manufacturing requires CapEx-heavy clean rooms, supply chain management for biocompatible materials, and quality control for physical devices. Software requires different talent, data scientists, UX designers, cloud infrastructure engineers, and different margin structures. Dexcom must maintain its 70% hardware margins while simultaneously building software capabilities that may initially generate lower revenue per user but offer higher lifetime value through platform stickiness. The transition risks alienating the manufacturing culture that built the duopoly while failing to attract the software talent necessary to compete with consumer tech giants.
The cultural transformation extends to risk tolerance. Medical device companies optimize for regulatory certainty and error-free manufacturing. Software companies optimize for iteration speed and network effects. Dexcom must now do both, maintaining FDA compliance for sensors while pushing over-the-air algorithm updates and mobile app features that move at Silicon Valley speed. The organizational friction between these modes consumes management bandwidth and capital. If Dexcom fails to execute the software transition, it remains a high-margin consumables business with a expiration date determined by the arrival of non-invasive monitoring. If it succeeds, it captures the data layer of diabetes management, becoming indispensable even if the sensor hardware eventually commoditizes.
The Assumption of Invasion
Beneath every strategic decision lies a single fragile assumption: that subcutaneous invasion remains necessary for clinical-grade accuracy for the next decade. Dexcom’s stock price, its R&D priorities, and its manufacturing investments all assume that non-invasive alternatives will remain in the realm of research laboratories and failed startups.
The physics are challenging. Glucose has a weak spectroscopic signature compared to water and other tissue components. Interstitial fluid measurements require either fluid extraction through microneedles or complex optical paths through skin. Yet Apple’s exploratory work on silicon photonics, the progress of companies like Know Labs in infrared spectroscopy, and continued research into glucose-binding hydrogels suggest that the 15% MARD threshold may eventually fall without breaking skin. The clinical standard could shift not because invasive monitoring fails, but because non-invasive becomes “good enough” for the majority of patients who prioritize convenience over absolute precision.
If this occurs, Dexcom’s manufacturing scale becomes a stranded asset. The company cannot pivot to non-invasive technology without abandoning its core competency and regulatory advantages. The duopoly dissolves into a contestable market where distribution, brand, and user interface matter more than electrochemical signal processing. Dexcom would face competition from Samsung, Apple, and Amazon, ompanies with consumer trust, retail presence, and balance sheets capable of subsidizing health monitoring to capture data ecosystems.
The Patient as Balance Sheet
The filament under the skin connects to the income statement. Every ten days, the patient performs the manufacturing labor of insertion, calibration, and replacement, turning their body into a recurring revenue stream. Dexcom’s business model works because diabetes is inexorable, because insulin dosing requires precision, and because insurers fear the hospital bill more than they resent the $2,000 annual sensor cost.
Yet the model contains a paradox. To grow into its valuation, Dexcom must escape the narrow confines of the insulin-intensive population without destroying the premium pricing that funds its algorithmic superiority. It must integrate deeply with insulin delivery systems to create switching costs, without becoming a captive component of larger platforms. It must defend invasive technology’s accuracy advantage while preparing for a software-defined future that may not require invasion at all.
The company stands at the intersection of medical device economics and consumer health ambition, carrying the weight of manufacturing complexity while attempting to pivot toward algorithmic elegance. Whether Dexcom becomes the platform that digitizes metabolic health, or merely the last great manufacturer of disposable filaments before optical sensors take over, depends on how long the duopoly can hold, how effectively the algorithmic moat widens, and whether insurance companies continue to believe that real-time glucose data justifies premium pricing for the worried well as much as for the critically ill. The patient wears the device; the investor wears the risk.
The mechanics of insurance gatekeeping operate through invisible bureaucratic chokepoints that Dexcom cannot directly control. Prior authorization requirements, documentation proving medical necessity, function as friction layers deliberately engineered by payers to slow adoption in marginal populations. For a Type 1 patient, prior auth is routine: the diagnosis code alone suffices. For a pre-diabetic or non-intensive Type 2 patient, the process requires attestation that the patient experiences recurrent hypoglycemia, demonstrates glucose variability exceeding specified thresholds, or has failed alternative monitoring protocols. Each additional administrative step winnows the addressable market. Dexcom’s sales force spends increasing hours navigating these bureaucratic thickets, converting clinical indications into reimbursement codes that satisfy actuarial skepticism.
The economics of this gatekeeping are stark. Commercial insurers operate on medical loss ratio floors mandated by the Affordable Care Act; they must spend 80-85% of premiums on medical claims. This creates a zero-sum calculation where every dollar spent on Dexcom sensors reduces dollars available for other claims. Pharmacy benefit managers (PBMs), who control formulary placement for the pharmacy channel where Dexcom increasingly distributes, extract rebates in exchange for preferred tier placement. Dexcom’s 70% gross margin provides headroom for such rebates, but each percentage point surrendered to secure coverage for expansion populations directly reduces the R&D budget available for algorithm refinement. The company walks a tightrope where growing volume requires sacrificing margin, yet margin erosion threatens the technical superiority that justifies the volume in the first place.
Medicare presents its own structural constraints. The Centers for Medicare & Medicaid Services (CMS) approved CGM coverage for insulin-using beneficiaries in 2017, expanded to non-insulin-using Type 2 patients with a history of problematic hypoglycemia in 2023. Yet Medicare reimbursement operates through durable medical equipment (DME) channels distinct from pharmacy benefits, creating a bifurcated distribution system that requires separate sales infrastructure, distinct billing codes, and compliance with anti-kickback statutes that prohibit inducements to prescribing physicians. The DME channel carries higher administrative costs and slower payment cycles than pharmacy distribution, compressing working capital efficiency as Dexcom penetrates deeper into the Medicare population. CMS’s price-setting authority, unilateral and politically sensitive, represents a perpetual sword of Damocles. If federal budget pressure intensifies, CMS could impose competitive bidding requirements or reference pricing against Abbott’s lower-cost Libre, instantly compressing Dexcom’s premium pricing power in a population segment representing 30% of current revenue.
The direct-to-consumer marketing campaign featuring Nick Jonas during Super Bowl LVII, costing an estimated $7 million for the media buy alone, represented a strategic inflection point that many analysts misinterpreted as mere brand building. In medical device economics, DTC advertising functions as a demand-generation tool intended to circumvent physician gatekeeping by creating patient pull. The strategy assumes that an activated patient, armed with celebrity endorsement and web-based education, will pressure their physician to prescribe despite clinical ambivalence or insurance resistance. For insulin-intensive populations, this pull merely accelerates inevitable adoption. For expansion populations, it risks creating a cohort of dissatisfied users whose clinical outcomes fail to justify the cost.
Consider the behavioral economics of non-intensive Type 2 diabetes. These patients manage condition through oral medications, lifestyle modification, and periodic A1C testing. Their daily glucose variability is lower; the clinical utility of real-time minute-by-minute data diminishes proportionally. When DTC marketing induces such patients to demand Dexcom, several failure modes emerge. First, adherence drops: the hassle of sensor insertion, adhesive maintenance, and alarm fatigue outweighs perceived benefit for patients not facing immediate hypoglycemic risk. Second, behavioral modification fails to materialize: simply knowing one’s glucose level does not automatically induce dietary discipline or exercise compliance. Third, insurance denial creates negative brand equity: patients who see the advertisement, crave the technology, then discover their insurer categorizes CGM as “investigational” for their diagnosis code, associate Dexcom with aspirational unattainability rather than medical necessity.
Dexcom’s customer acquisition cost (CAC) in these expansion populations likely runs 3-4x higher than in core insulin-intensive markets. The DTC spend must overcome physician skepticism, insurance resistance, and lower intrinsic product-market fit. If conversion rates disappoint, the company faces a classic SaaS trap, growth metrics masking unit economics deterioration, except the consumables model lacks the high gross margins of software to absorb CAC inefficiency indefinitely. The Super Bowl advertisement bought millions of impressions; it may also have bought thousands of frustrated patients whose social media complaints about insurance denials or adhesive failures travel further than clinical efficacy data.

Abbott Laboratories occupies the value position in this duopoly with Libre, a flash glucose monitor that requires manual scanning rather than providing automatic real-time alerts. Libre’s cost structure, roughly 60% of Dexcom’s sensor price, reflects simpler electronics, no transmitter, and calibration-free operation that sacrifices some accuracy for convenience. Abbott has aggressively pursued pharmacy channel distribution with lower co-pay structures, capturing 3.5 million patients to Dexcom’s 1 million by optimizing for price-sensitive, non-intensive populations where minute-by-minute alerts matter less than periodic trending data.
The competitive dynamic resembles the early smartphone market: Dexcom as Apple, commanding premium pricing through superior user experience and ecosystem integration; Abbott as Android, winning on unit economics and distribution breadth. Yet unlike consumer electronics, medical device markets resist pure price competition because physician prescribing habits and insurance formularies create inertia. Endocrinologists trained on Dexcom’s interface, familiar with its alert algorithms, and integrated with Tandem pumps face cognitive switching costs that transcend mere price comparison. However, if Abbott achieves real-time alert parity with Libre 3 and secures insulin pump integration, Omnipod has announced compatibility testing, the differentiation collapses to price. In such a scenario, pharmacy benefit managers possess leverage to demand “parity pricing” where Dexcom must match Abbott’s reimbursement rates or face exclusion from formularies. A 30% price cut applied to Dexcom’s revenue base would eliminate approximately $1 billion in annual gross profit: oughly the company’s current R&D expenditure.
The bear case regarding non-invasive monitoring requires specific technical examination rather than vague technological anxiety. Several competing modalities approach clinical viability on distinct timelines. Silicon photonics approaches, exemplified by Apple’s exploratory work and startups like Rockley Photonics, attempt to detect glucose through optical absorption spectroscopy in the near-infrared range. The physics challenge involves distinguishing glucose’s weak spectral signature amid interference from water, lipids, and proteins in dermal tissue. Current prototypes achieve 20-25% MARD in controlled settings, nsufficient for insulin dosing decisions but approaching utility for trend monitoring. If these systems reach sub-15% MARD through machine learning signal processing and multi-wavelength analysis, they could capture the pre-diabetic and non-intensive Type 2 markets Dexcom covets, effectively ceding Dexcom to the declining population of insulin-dependent patients while growth accrues to optical sensors.
Transdermal microneedle arrays represent another threat vector. Companies like Biolinq and Nova XS develop electrochemical sensors that penetrate only the stratum corneum, the dead outer skin layer, rather than subcutaneous tissue. These devices would eliminate the foreign body response that limits current sensor longevity to 10-14 days, potentially enabling month-long wear or permanent implantation. While still invasive at the microscopic scale, they bypass the manufacturing complexity of Dexcom’s filament insertion mechanisms and could be produced through standard semiconductor fabrication processes, opening manufacturing to contract manufacturers with no medical device expertise.
Most proximate is the smart contact lens approach pursued by Google Verily and others. Glucose concentration in tear fluid correlates with blood glucose, though with temporal lag and calibration challenges. A contact lens integrating wireless transmission and glucose-sensitive hydrogels would eliminate skin adhesion issues entirely, capture the Asian market where contact lens wear rates exceed 30%, and integrate naturally with augmented reality platforms. If such devices achieve FDA approval for trend monitoring, if not precise insulin dosing, they would commoditize the non-intensive monitoring market overnight, leaving Dexcom with only the highest-acuity patients who require subcutaneous precision.
The organizational transformation required for Dexcom’s pivot from hardware manufacturer to software platform entails economic risks rarely quantified in investment models. Medical device engineering cultures reward precision, documentation, and regulatory compliance, indsets antithetical to the “move fast and break things” ethos of consumer software development. Dexcom’s acquisition of various digital health startups in recent years, companies specializing in data analytics and patient engagement, creates integration friction as distinct compensation structures, equity vesting schedules, and technical debt collide with Dexcom’s established manufacturing operations.
Software platform economics require different capital allocation discipline. Hardware manufacturers maximize return on invested capital (ROIC) by optimizing manufacturing throughput and inventory turns. Software platforms maximize lifetime value (LTV) by accepting near-term losses on customer acquisition to capture data network effects. Dexcom must simultaneously maintain the 70% hardware margins that satisfy public market expectations while investing in software capabilities, predictive algorithms, API development, care provider dashboards, that may not generate direct revenue for years. The capital structure cannot easily fund both without dilution or debt, yet the strategic necessity demands both.
Human capital markets compound this tension. Dexcom’s headquarters in San Diego competes for software engineering talent against Qualcomm and biotech startups, while lacking the prestige and compensation velocity of Bay Area technology giants. Attracting machine learning PhDs to a medical device company requires cultural transformation that risks alienating the bioengineers who built the sensor platform. If the software pivot fails, Dexcom retains a valuable but declining hardware business; if the hardware culture dilutes prematurely, manufacturing quality, the bedrock of the duopoly, could slip, creating openings for Abbott or Medtronic to capture high-acuity patients through reliability advantages.
International expansion presents additional structural constraints obscured by TAM calculations. Dexcom’s current addressable markets, North America and Western Europe, feature reimbursement infrastructure capable of supporting $2,000 annual monitoring costs. Penetrating China, India, or Latin America requires price points an order of magnitude lower, necessitating entirely different manufacturing architectures. The G7 sensor’s miniaturization enables cost reduction, but reaching $200 annual price points while maintaining 70% margins would require manufacturing scale and automation levels that risk quality control lapses reminiscent of Theranos’s industrial failures, r acceptance of 40% margins that collapse the valuation multiple.
China’s domestic medical device champion, POCTech, already markets CGMs at fraction of Dexcom’s pricing through government-subsidized distribution. While current accuracy lags Dexcom’s standards, China’s regulatory environment favors domestic champions, and the scale of China’s diabetic population, 140 million diagnosed, enables rapid iteration through real-world evidence generation. Dexcom cannot compete on price in these markets; it can only compete on accuracy and ecosystem integration, but Chinese electronic manufacturing ecosystems could replicate hardware capabilities faster than Dexcom can adapt its software platform to Mandarin-language healthcare workflows and state-controlled insurance reimbursement.

The closed-loop artificial pancreas ecosystem, Dexcom’s deepest moat, contains hidden fragilities often obscured by technological enthusiasm. Tandem Diabetes Care’s Control-IQ algorithm uses Dexcom glucose data to adjust insulin delivery automatically, reducing patient cognitive burden and improving outcomes. Yet this integration creates bilateral dependency. Tandem represents approximately 40% of Dexcom’s insulin pump integration volume; if Tandem were acquired by Medtronic or Abbott, or if Tandem’s business model failed under competitive pressure from Omnipod’s tubeless system, Dexcom’s ecosystem moat narrows abruptly. Conversely, if Tandem achieves sufficient scale to demand exclusive supply agreements or price concessions, Dexcom’s bargaining power erodes.
The firmware-level integration required for closed-loop operation also complicates regulatory compliance. When Dexcom updates its algorithm, the FDA must validate the entire closed-loop system, including Tandem’s insulin delivery response. This creates coordination costs and slows innovation velocity. If a software bug in glucose prediction causes insulin overdose, liability distributes opaquely between sensor manufacturer and pump manufacturer, potentially exposing Dexcom to product liability risks beyond its core competency.
Insulet’s Omnipod represents the alternative integration path: tubeless patch pump that appeals to patients seeking discretion and freedom from tubing. Dexcom’s announced integration with Omnipod 5 (the automated version) diversifies ecosystem dependency, but Omnipod’s manufacturing constraints have historically limited supply, creating allocation tensions where Dexcom’s sensor availability depends on Insulet’s production capacity. These interdependencies transform Dexcom’s unit economics from standalone sensor margins to complex revenue-sharing arrangements where value capture leaks to pump manufacturers.
The ultimate economic variable remains the durability of the consumables model itself. Dexcom’s valuation assumes perpetual ten-day replacement cycles, yet sensor longevity improvements threaten this cadence. If manufacturing advances enable 30-day wear, technically feasible with improved biocompatible materials and enzyme stabilization, revenue per patient declines by two-thirds unless pricing increases proportionally, which insurance companies would resist. Dexcom thus faces the innovator’s dilemma familiar to razor-blade manufacturers: improving the product destroys the business model. The company must thread a needle where incremental longevity improvements justify premium pricing without eliminating replacement frequency entirely, or pivot toward software subscription models where per-patient revenue depends on data value rather than hardware consumption.
Data monetization, selling aggregated, de-identified glucose trends to pharmaceutical companies, insurers, or researchers, offers theoretical revenue diversification but faces regulatory and ethical constraints that limit scale. HIPAA compliance requires expensive infrastructure; patient consent for data commercialization remains legally ambiguous; and the value of glucose trend data to pharma companies, while real, likely measures in tens of dollars per patient annually rather than the hundreds required to replace sensor revenue. Dexcom cannot rely on data as a primary economic engine without transforming into a fundamentally different business: ne regulated as a data broker rather than a medical device manufacturer, subject to GDPR, state privacy laws, and cybersecurity liabilities foreign to its current risk profile.
The bear case culmination envisions Dexcom as a successful medical device company trapped in the wrong strategic epoch: a premium manufacturer of invasive sensors in an industry transitioning to non-invasive monitoring, a high-margin hardware business attempting software platform economics, a duopoly player facing price compression from insurance gatekeepers no longer convinced of cost savings in expansion populations. In this scenario, the company retains the insulin-intensive core, a stable, profitable, slowly growing business serving 4 million patients globally, but fails to capture the 40 million pre-diabetic and non-intensive Type 2 patients necessary to justify growth multiples. The stock re-rates from growth to value, trading at medical device multiples (15-20x earnings) rather than platform multiples (30-40x revenue), while management allocates cash to share buybacks rather than transformative innovation.
Such outcomes are not certainties but structural possibilities embedded in the current model. The filament under the skin remains the standard of care, the algorithm maintains its accuracy advantage, and the insurance reimbursement dam holds back price pressure while permitting gradual market expansion. Yet each of these conditions represents an assumption under pressure from technological alternatives, economic gatekeepers, and organizational transformation risks. The patient continues inserting the sensor, disposing of it, inserting another: mechanical ritual generating reliable cash flows until the ritual itself becomes obsolete.
When that obsolescence arrives, whether through optical sensors, prolonged enzyme stability, or payer revolt, the stranded manufacturing assets tell their own story. The clean rooms in Mesa, Arizona, optimized for ten-day sensor batches, cannot be repurposed for semiconductor wafer production. The sterilization equipment, validated for specific biocompatible polymers, becomes scrap metal. The accumulated process knowledge, how to calibrate enzymatic activity across temperature ranges, how to adhesive-laminate without inducing skin reaction, transfers poorly to software engineering or data analytics. Dexcom would face the economic fate of film camera manufacturers confronting digital imaging: not immediate bankruptcy, but a long, margin-compressing decline as the installed base shrinks by attrition rather than mass defection.
Consider the specific trigger: a 2026 CMS decision removing CGM coverage for non-insulin-using Type 2 patients after the agency’s actuaries determine that hospitalization reductions fail to materialize in real-world data. Overnight, Dexcom’s addressable market contracts by fifteen percent. Pharmacy benefit managers, sensing weakness, demand parity pricing with Abbott’s Libre, compressing gross margins from seventy to fifty percent. The stock drops forty percent in a month not because the business fails, but because the terminal value assumption, perpetual ten-day replacement cycles expanding into pre-diabetes, collapses. The company survives, profitable but pedestrian, collecting cash from an aging cohort of Type 1 patients while Apple and Abbott capture the next generation. The ritual ends not with a bang, but with a copay.