Electrode Material Selection Governs Signal Quality More Than Amplifier Design
That biological-electrical negotiation begins with the understanding that dry electrodes do not make electrical contact in the way solder joints do. When designing a clinical ECG patch or consumer heart rate monitor, you are creating a temporary electrochemical cell. The skin presents an impedance of 10kΩ to 1MΩ depending on hydration, while the electrode metal establishes its own half-cell potential. Without the conductive gel used in hospital settings, your electrode must use microporous metals, conductive polymers, or hydrogel composites to bridge this gap without irritating the skin over days of wear.
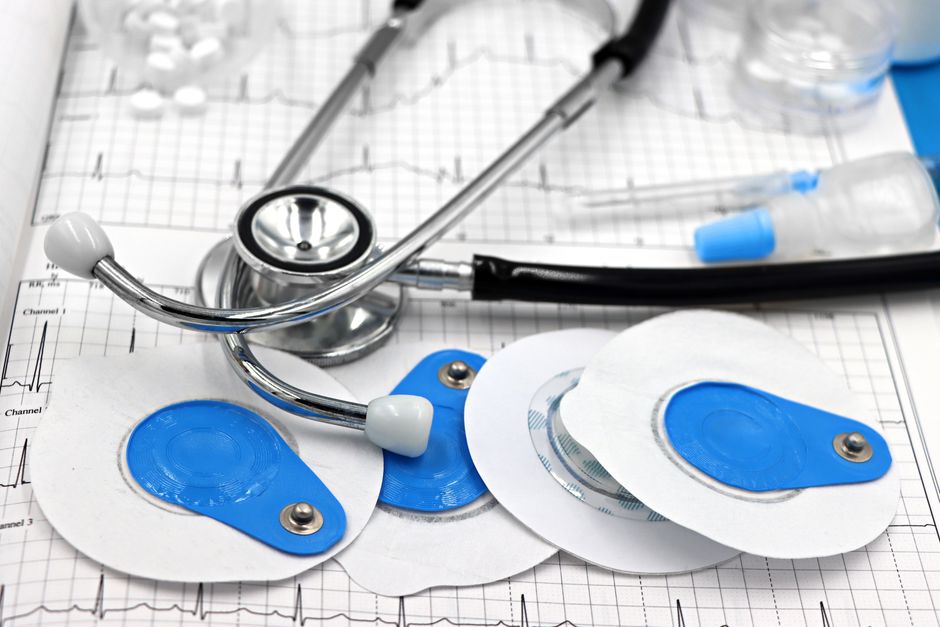
Photo by Marta Branco on Pexels
Silver-silver chloride ink printed on flexible substrates offers stable reference potentials but corrodes when exposed to sweat chloride ions, creating drift that mimics cardiac baseline wander. Stainless steel resists corrosion but generates polarization voltages that swamp the 1-2mV P-wave you need to detect atrial fibrillation. Conductive polymers like PEDOT:PSS offer biocompatibility and low impedance but degrade under mechanical flexure. The mechanical properties matter as much as the electrical ones; a rigid electrode pressing against compliant skin creates air gaps that introduce capacitive coupling artifacts. You are designing a temporary electrochemical cell that happens to measure cardiac depolarization, and that cell requires the same attention to ionic transport and redox stability as a battery chemistry. Which electrode material you choose determines whether your device measures a P-wave or baseline noise.
Mechanical Compliance Defeats Motion Artifact Before Signal Processing Can
Once that electrochemical interface stabilizes, cardiac monitoring wearable design must survive the fact that the human body is a moving, compressing, sweating machine. Motion artifact exceeds the reach of digital signal processing alone. It originates at the mechanical interface where the electrode and skin experience differential acceleration. During running, the skin at the wrist can experience 2g accelerations while the underlying bone moves differently, creating shear forces that generate triboelectric noise resembling ventricular tachycardia in the trace.
Solving this requires mechanical compliance that follows skin strain without sliding. Suspended electrode architectures, where the sensing element floats on an elastomeric suspension within the housing, maintain galvanic contact while the device chassis shifts with respect to the dermis. Some wearable cardiology device designs use gimballed electrode assemblies that maintain normal force during wrist rotation. Reference electrodes placed adjacent to active leads allow common-mode rejection of motion artifacts, but only if the mechanical design maintains consistent spacing during flexion. Clinical ECG patches use adhesive hydrogels to eliminate relative motion entirely; consumer devices must achieve similar stability through geometry and distributed spring forces. A 50mg inertial load on a rigid electrode creates more signal corruption than a 5mV arrhythmia; your mechanical compliance strategy determines whether your device detects cardiac events or merely captures movement.
FDA Validation Locks Electrode Geometry Before industrial design Finalizes
If mechanical compliance preserves signal integrity, that signal must eventually meet the standards of an FDA cardiac device seeking clearance for clinical decision-making. A 510(k) submission for arrhythmia detection requires validation against a 12-lead Holter monitor across demographic variations in skin impedance, body mass index, and cardiac anatomy, often requiring 10,000 patient-hours of annotated data.
Photo by Marta Branco on Pexels
This means your electrode geometry and analog signal chain must be locked for validation before industrial design finalization. You cannot iterate the distance between leads or the sampling rate after usability testing suggests a smaller form factor. Single-lead ECG configurations can detect atrial fibrillation but miss axis deviations or ischemic changes that require vector analysis across multiple leads. The physical spacing of electrodes determines which cardiac vectors you can sample, which determines which conditions you can claim to detect, which determines your classification as a Class II medical device versus a general wellness product. Your enclosure design serves the electrical vectors required for clinical validation, not ergonomic preference.