Motion Artifact Masks Ischemic ST-Segment Changes
Ambulatory ECG systems have traditionally prioritized noise reduction through digital signal processing. In a hospital setting, this works; if a telemetry lead loses contact during a treadmill test, the technician stops the belt and reapplies the electrode. In remote cardiac rehab, the patient is walking the dog or climbing stairs. The motion artifact introduced by skin deformation and cable sway occupies frequency bands that overlap with the ST-segment. Aggressive software filtering to remove baseline wander and muscle noise inevitably degrades the 1-millimeter ST-elevation resolution required to detect demand ischemia. This means the ECG wearable cardiac rehab system cannot rely on post-processing to clean up poor mechanical contact. The signal integrity must be preserved at the interface level, which shifts the engineering burden from firmware to the physical marriage between sensor and skin.

Photo by Los Muertos Crew on Pexels
Textile Architecture Replaces Adhesive Patch Electrodes
If the electrode moves relative to the dermal layer during respiration or shoulder rotation, the impedance fluctuates and the ECG trace becomes unusable. Adhesive patches like the iRhythm Zio provide excellent short-term fixation, but the ISO 10993 biocompatibility profile for week-long wear differs fundamentally from the six-week cardiac rehabilitation protocol. Patients with post-surgical scar tissue from median sternotomy present additional impedance variables that adhesives exacerbate.
This is why textile-integrated systems, compression shirts with conductive fabric electrodes, have emerged as the viable architecture for this category. The garment itself becomes the sensor mount, applying consistent pressure across the precordial leads independent of body position. However, compression levels measured in millimeters of mercury must balance ECG stability against patient tolerance. Too loose, and motion artifact returns; too tight, and the patient experiences heat buildup and skin irritation that drives abandonment. A conductive yarn specification chosen for electrical conductivity may fail within three washes due to silver ion oxidation, rendering the garment unusable before the rehab protocol ends. Because a material decision made for signal fidelity becomes a patient compliance decision within the first hour of wear, the textile engineering and electrical engineering must be solved simultaneously.
Adherence Collapses When the Device Signals Medical Fragility
The moment a post-surgery monitoring wearable user realizes their chest strap is visible through their shirt during a video call with colleagues, the compliance math changes. Cardiac rehab occurs in living rooms, not clinics. The patient is not a professional athlete accustomed to chest-mounted sensors; they are a 68-year-old recovering from a cardiac event who associates medical hardware with fragility.
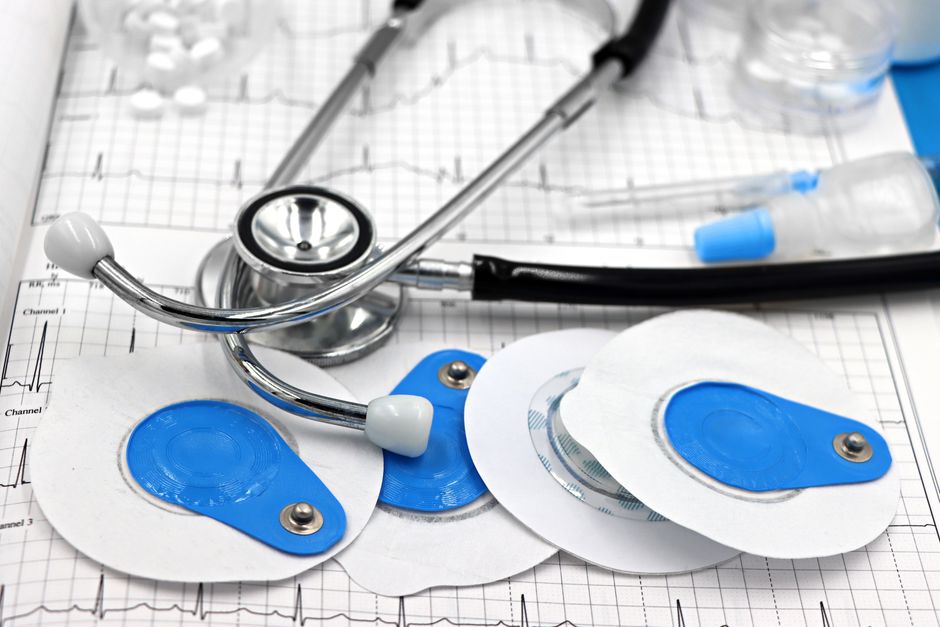
Photo by Marta Branco on Pexels
The device must survive the 45-minute exercise bout, sweat, temperature gradients, and the psychological weight of constant illness monitoring. Consumer fitness wearables like Whoop have proven that users will tolerate chest-worn sensors for performance optimization, but the aesthetic language of medical devices triggers different behavior. If the telehealth cardiac device resembles hospital equipment, adherence drops after week two, long before the six-week program concludes. Battery life extending beyond seven days reduces charging friction, but the battery mass increases garment weight, which increases perceived exertion during walking tests. The teams that solve this trade-off treat the industrial design as behavioral intervention, minimizing the “SICK role” stigma while maintaining the clinical data stream required for remote physiologic monitoring reimbursement codes.